NOCD is a virtual therapy platform for specialized OCD treatment that has grown
exponentially over the years. As a full-time designer there I also worked on supporting their
internal tools, and this is what happened when the thing
that stopped scaling was how the company trains its own clinicians.
One platform, one loop
Training at Noto used to live in four different tools. Now each step
hands to the next, and what the last one sees changes what the first one plans.
Plan
Cohorts arrive from hiring, and a whole schedule books in one pass.
Build
Courses made of lessons, live sessions, tasks and AI practice.
Assign
One course, or months of onboarding, to a person or a cohort.
See
Completion, attendance, and the skills to work on next.
Role
Sole designer, end to end: research through release, and the improvements after it
Team
Process subject matter expert, on research
4 developers
Clinical stakeholders
Senior leadership
Timeline
3 months, design to MVP
Outcome
110+ therapists onboarded every month across the two brands
This system was built within Noto, the parent company behind both NOCD and Rebound, using
NOCD's process as the original blueprint.
Context
NOCD scaled from onboarding 20 therapists a month to 100, with a training team of six. The
old process had not scaled with it: a 100+ page living Word doc as the itinerary, Zoom links
trainers updated by hand across three locations, and feedback that landed in Slack threads and
spreadsheets trainers filled out but managers rarely saw again once training ended. New
therapists routinely spent 8+ hours in Zoom just to stay coordinated.
The coordination did not happen quietly in the background either. Chasing one missing
person ran through the clinical trainer, the clinical manager and the recruiter before it
reached the therapist, and it happened live, inside a session with twenty five other people
in it. That is the real number: not the time one person lost, but a room of twenty five
spending it on logistics instead of on training.
The training process, spread across multiple communication channels.
The real cost was not just time. We had no visibility into how a therapist was performing
during training, only after, once it showed up in treatment outcomes. Trainer notes existed,
but they stayed buried, never reaching the people who could act on them, spot patterns, or
build personalized training recommendations from them.
We needed a system that surfaced training performance early and kept it visible, not one
that let it disappear the moment training ended.
Role
I led the research and design of the platform end to end. Working with a Process Manager, I
mapped the entire onboarding process company-wide, interviewing the training team,
credentialing, clinical leadership, marketing, recruiting, and therapists' direct managers to
understand every dependency new hires had to move through. From that research I identified
where the biggest opportunities were, aligned with leadership and engineering on priority,
then took the findings forward to conceptualize and design the platform myself.
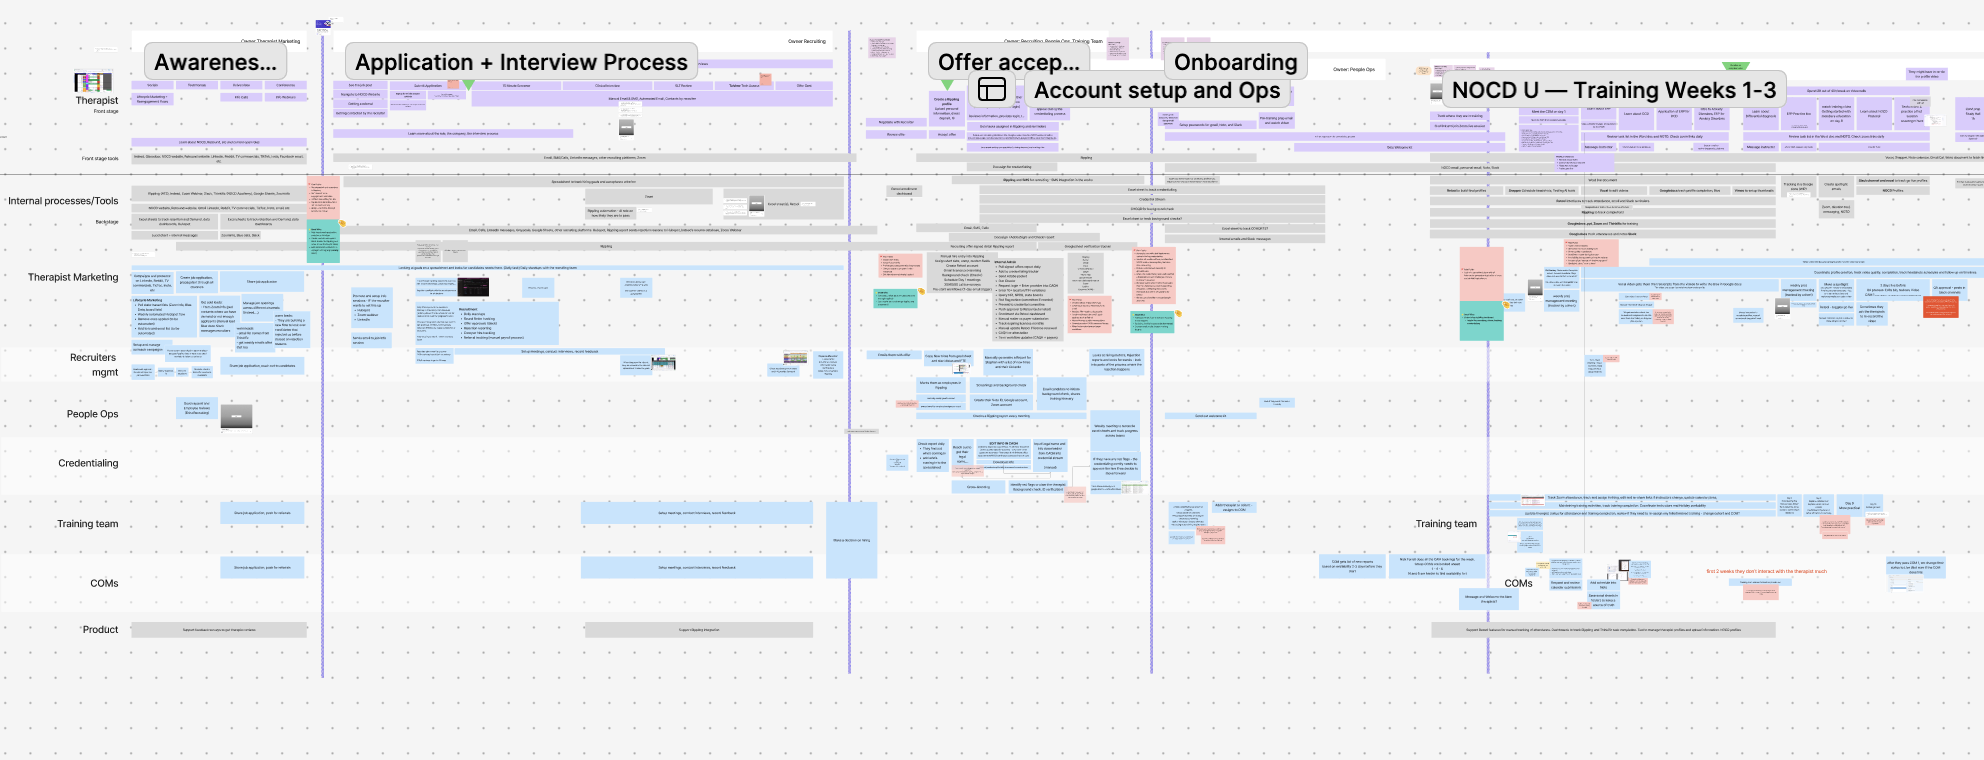
Snapshot of the service blueprint I created, with all internal processes
synthesized after user interviews.
Vision
The bigger win was not any single interface, it was making the process scalable and
transparent. Clear links between teams, and information that did not get lost once it was
captured, meant training, clinical, credentialing and the therapists themselves could all stay
focused on one thing: building a learning environment that actually prepares people to help
members with OCD.
Solution
⋮BeforeAfter
Turn your phone sideways for a bigger view
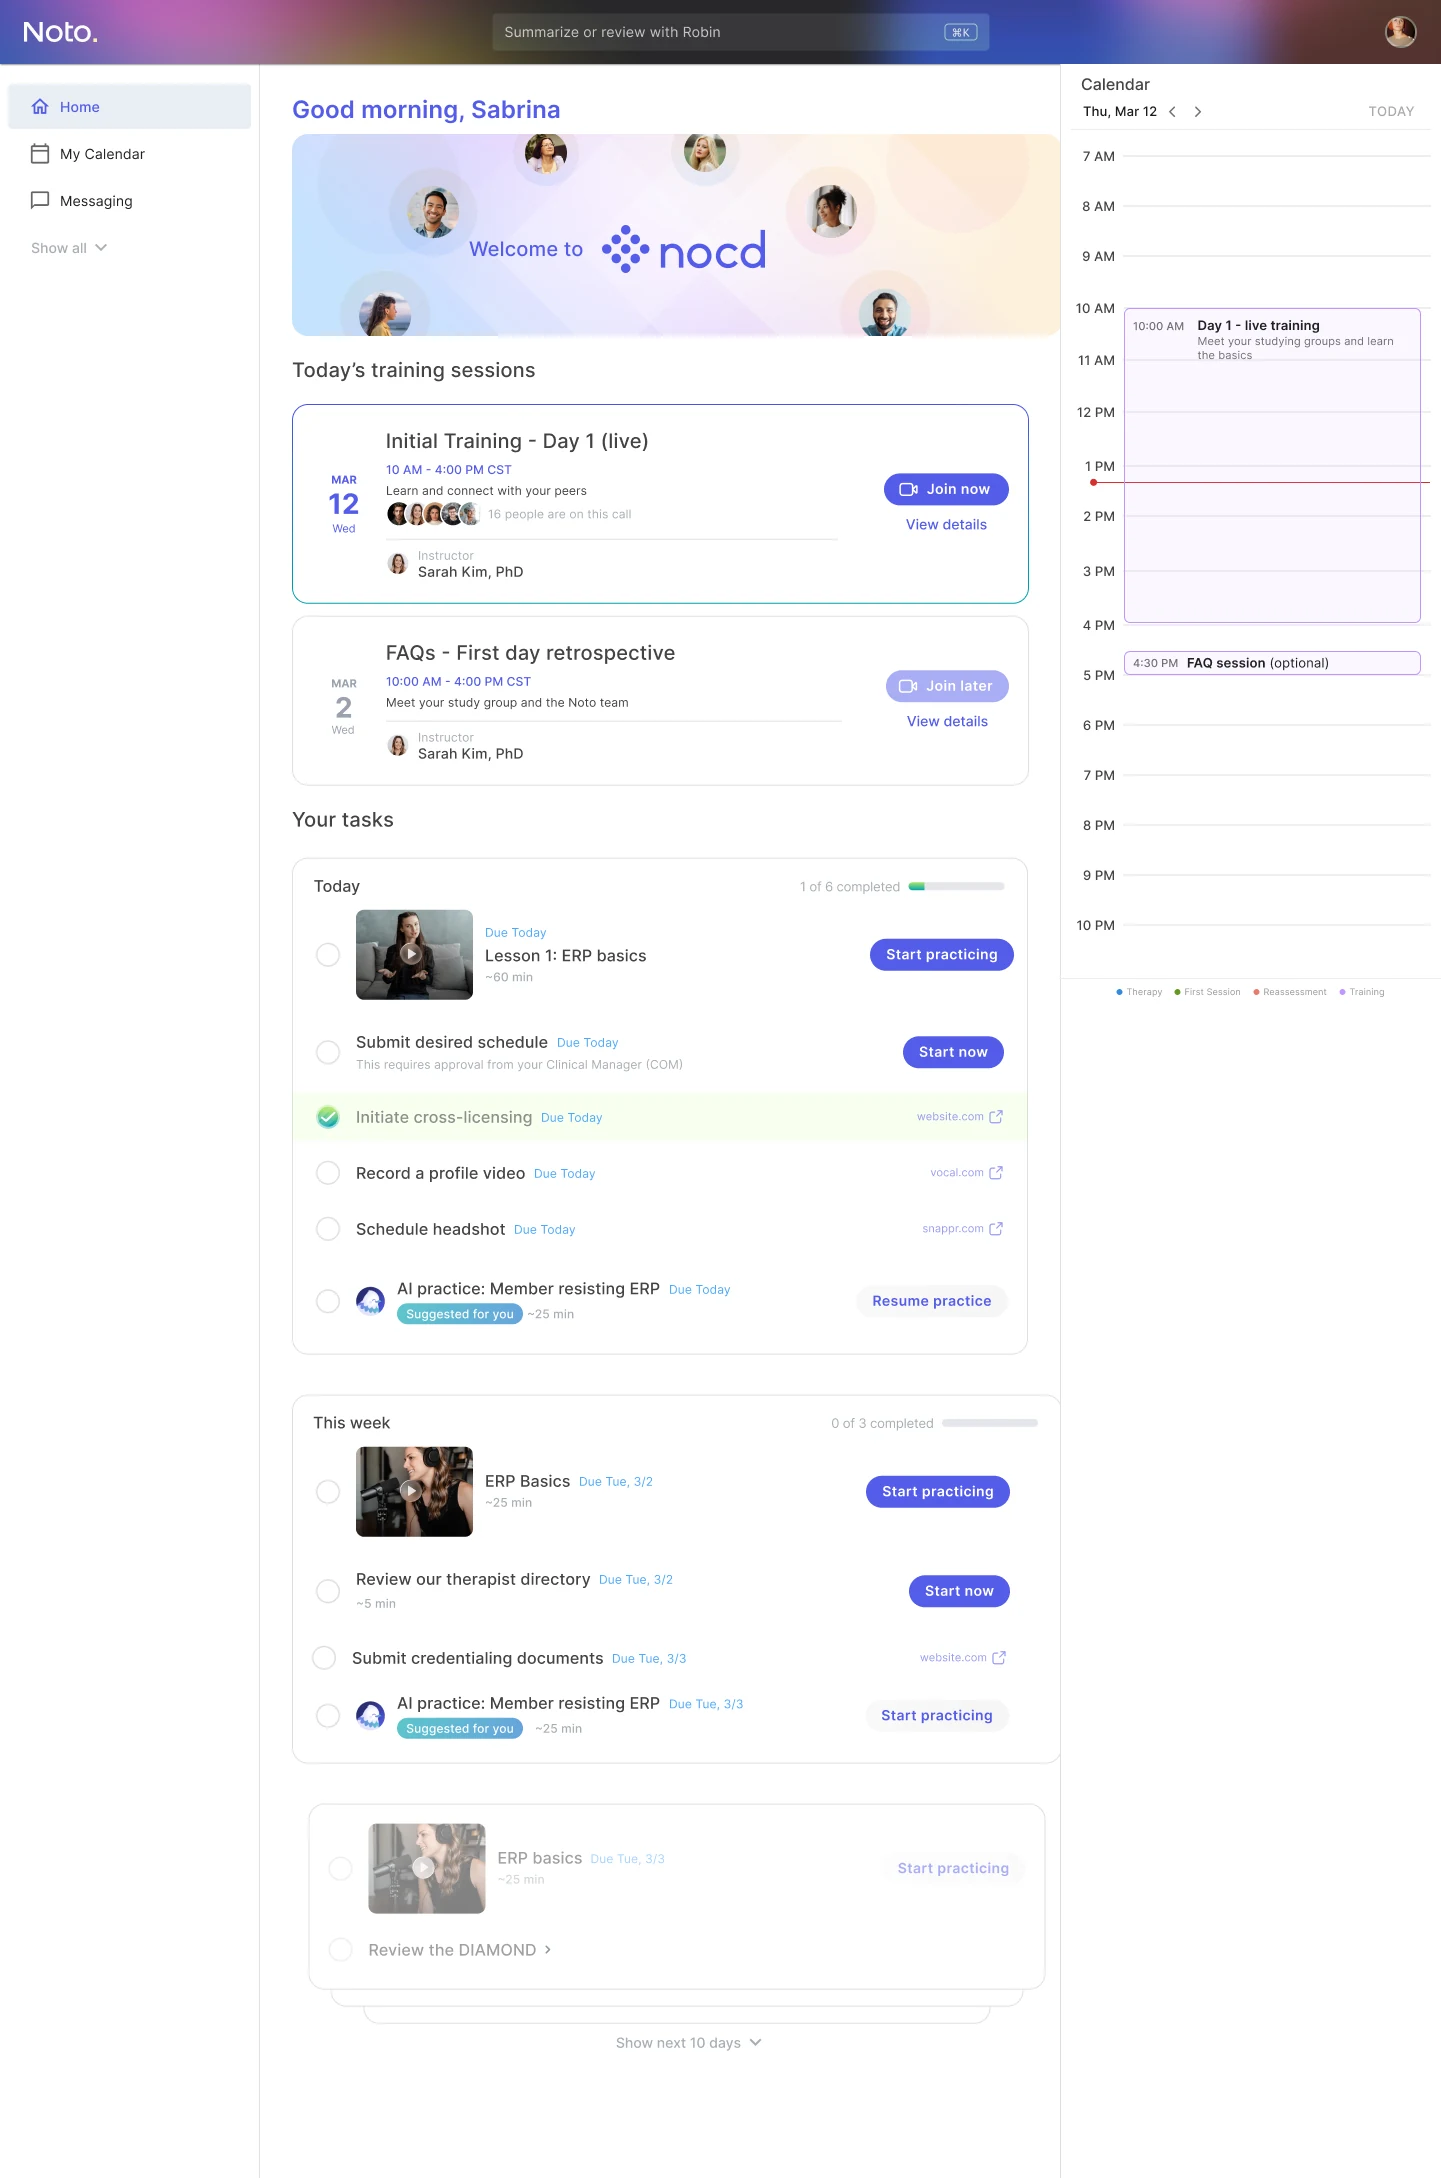
Day one, before and after. Drag to compare.
For new hires
The first two weeks needed a different interface from the rest of the journey, because the
therapist's reality during that window is completely different: dense, daily,
evaluation-driven. That is what shaped the UI for that phase specifically.
Before, therapists saw the same performance metrics used once they are live and taking
members, numbers that were meaningless before they were even equipped to earn them. We replaced
that with what they actually needed in the moment: a clear list of todos and completed tasks
with due dates, and a calendar view of mandatory events.
As they pass the week-two evaluation, training hours taper while their clinical hours ramp
up. Personalized re-training is part of that shift: using metrics and findings, we labeled our
content by the skill it is meant to improve, so the system can recommend training that directly
targets where a therapist has the most room to grow.
For the training team
Cohort lists now flow directly from hiring into the platform, with a default instructor set
per week per cohort, so trainers book an entire cohort's schedule in one pass instead of
scheduling per event, per week, per cohort across Google Calendar and other tools. Each trainer
gets their own calendar and live events inside the platform.
Attendance marks itself from Zoom logs. Trainers only verify it and add qualitative notes on
participation. Those notes now live on an internal therapist profile, visible to hiring
managers and accessible to our models, used to support recommendations, reviews and career
progression conversations.
Grouping new hires into a cohort and assigning their training in one pass.
Would you like to see more? Ask for a walkthrough of what is in
production, or a link to the prototype, at
joanargbelo@gmail.com.
The system underneath
Behind that, the content itself needed a model flexible enough to support how differently
training material gets used.
Bundle courses assign a full onboarding sequence at once: two or three months of
training in one go, with no editing required.
Individual courses can be built and reassigned freely, and contain any mix of tasks
(linked action items), lessons (async long-form text, links, quizzes, video), live sessions,
and AI practice modules. Live sessions split further into lectures, clinical assessments with
pass or fail and rubric-based evaluation logic, and study rooms for unstructured peer support
with no instructor required.
Any of these can also be assigned on its own, without needing a full course around it. That
is the part that made re-training possible later without anyone planning for it.
Building a course, and tagging it with the skills it is meant to improve.
Outcome
The platform now onboards 110+ therapists every month across NOCD and Rebound combined. Beyond
centralizing NOCD's own training data, Rebound, a specialty PTSD treatment platform acquired by
Noto, has been able to reuse existing materials while building out its own training framework
and clinical assessments on the same system. That is the clearest proof the model was flexible
enough: a second brand fitted inside it without a rebuild.
10%10%
of the therapist network moved into the target performance range in the first 30 days
110+110+
therapists onboarded every month, across the two brands
600+600+
items assigned in the first month, beyond the mandatory curriculum
50%+50%+
completion on that optional material
It is still early, live since July 2026, but
the signal so far is good. In the first month alone, over 600 items were assigned outside the
mandatory onboarding curriculum, with a completion rate above 50%. That is a monthly rate
rather than a running total, and it has only gone up since. Direct managers have started reusing
and building their own content to assign continuing education targeted at specific skills they
want a therapist to improve. That is exactly the personalized re-training the system was
designed to support, and they did not need to be told to do it.
Therapist performance
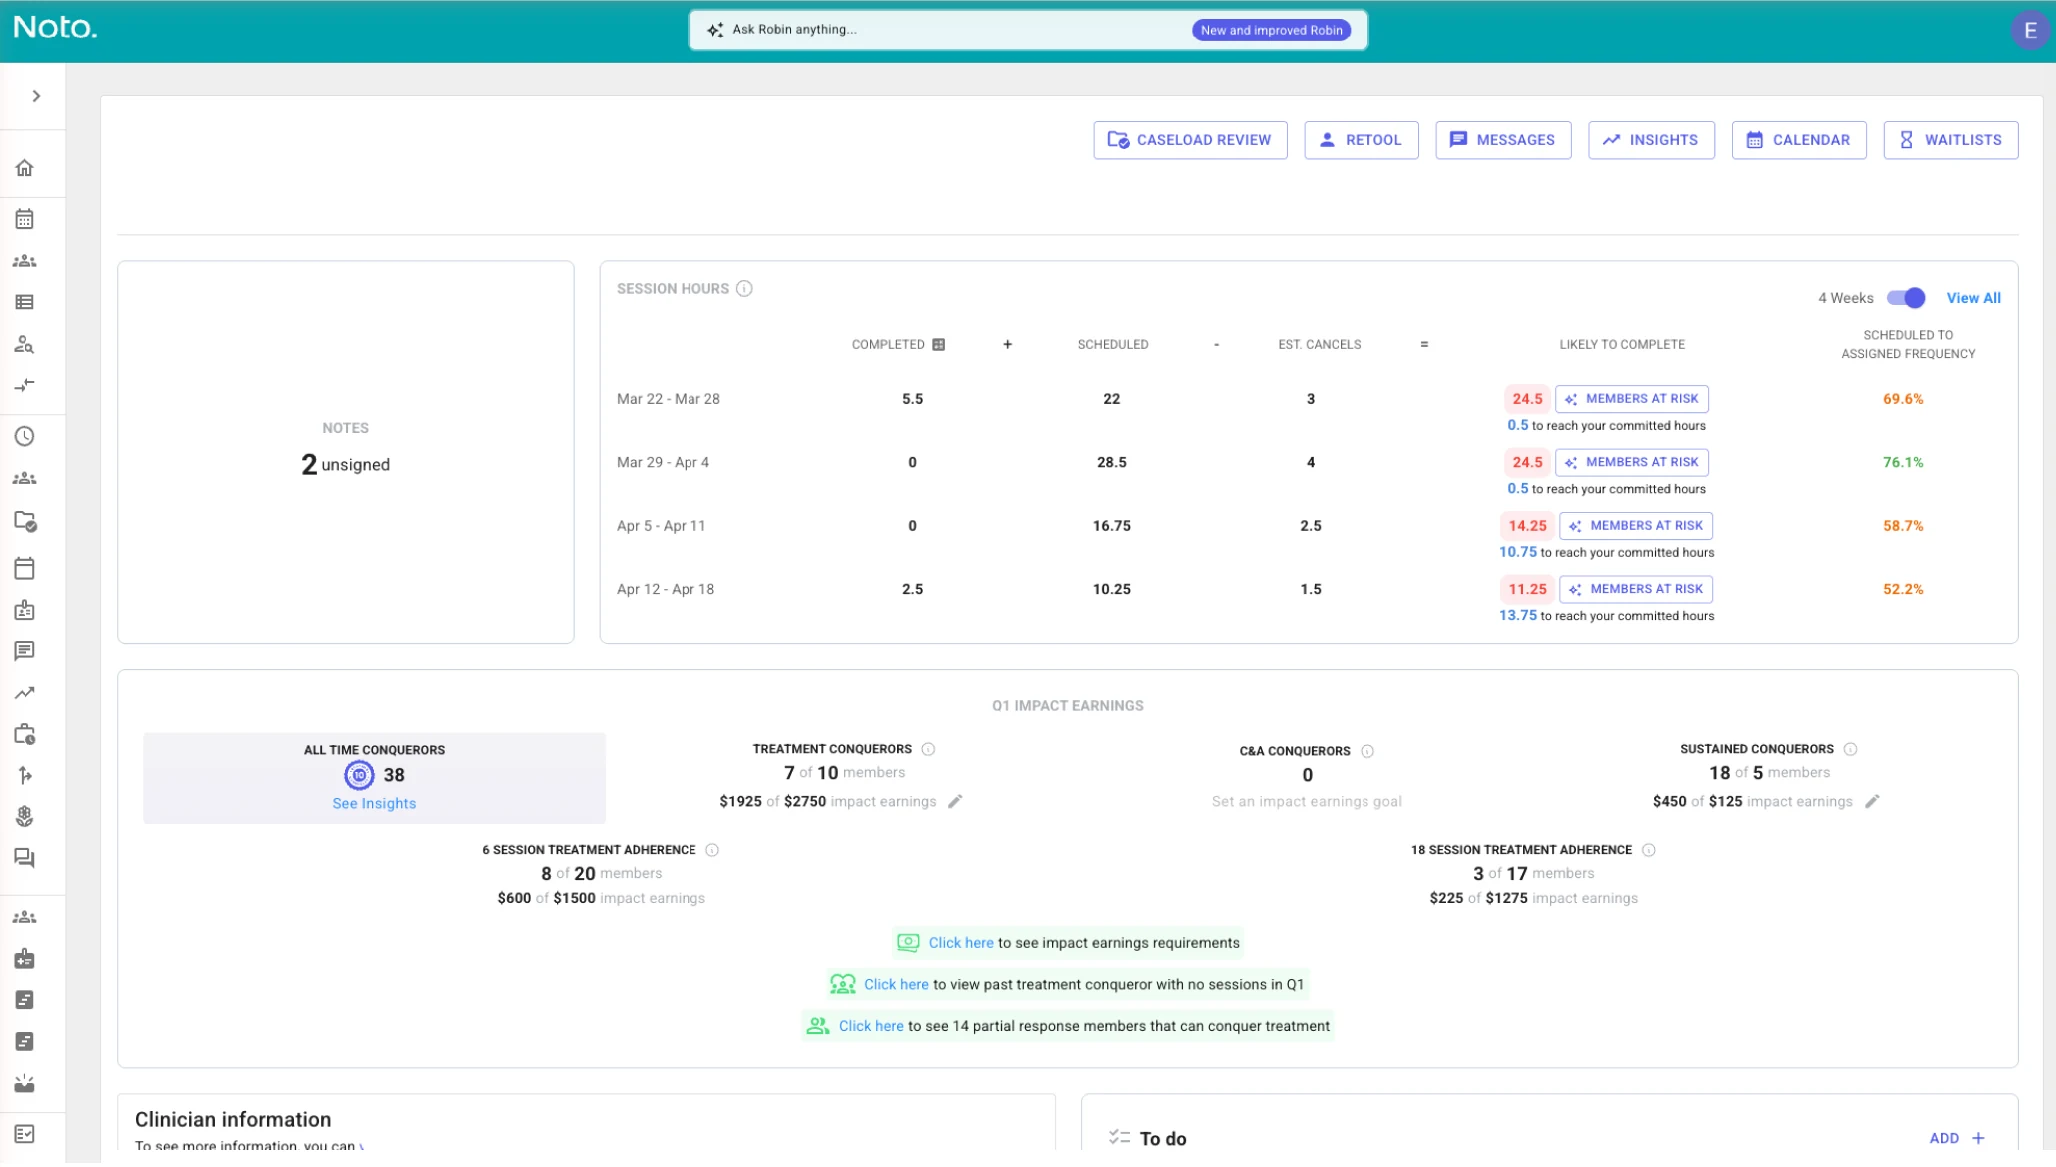
The platform also became the foundation for better internal tools. Training data now feeds
therapist profiles that bring a therapist’s metrics together, from member retention to
protocol adherence to required hours, so managers can see where each person is and what to
work on next. The platform is one of several initiatives working toward the same goal, and in
the first 30 days after it launched, 10% of the therapist network moved into the performance
range we want every therapist in.
Clinical outcomes
Clinical outcomes are the metric we care about most. I can’t publish that data, but it is
tracking positively: members are starting ERP (exposure and response prevention, the core treatment for OCD) as early as possible and sticking with it, therapists
are being more successful at adhering to the clinical protocol, and those numbers keep improving. We can also see training
completion and performance trends at scale, and tune the material and recommendations against
real data, instead of finding out something did not work only after it showed up downstream in
patient care.